Dr Wessam Mankoula, the agency’s head of emergency preparedness and response, described the possibility as one of several scenarios under investigation, emphasising that authorities had yet to establish a direct connection between the cases.
Nigeria is currently managing its first reported Ebola case in more than a decade, while Kenya has confirmed nine infections, including one death, in the ongoing outbreak.
Follow PenTalk News
Get breaking news, important updates and the latest stories directly on your phone.
Nigerian Patient Receiving Treatment in Isolation
The Nigerian patient, a 42-year-old Uganda-born woman residing in Abuja, is receiving treatment in isolation and has reportedly shown signs of improvement, according to the World Health Organization (WHO).
Switzerland’s foreign ministry confirmed to Reuters that the woman is married to a Swiss diplomat stationed in Nigeria. Her husband, who accompanied her during a trip to Uganda, has also been placed in isolation but has not developed symptoms.
Reports indicate that the woman returned to Nigeria on October 3 after spending approximately two and a half weeks in Uganda. Her journey included a stopover of about two hours in Addis Ababa, Ethiopia’s capital.
She reportedly developed symptoms four days after arriving in Abuja and sought medical attention at two private healthcare facilities before testing positive for Ebola on October 20.
Health officials are now reconstructing her movements and examining possible sources of infection, including whether her travel history overlaps with that of the Kenyan patient.
Kenyan Patient Died After Travelling Through Uganda
The Kenyan patient, a man who travelled from the Democratic Republic of Congo (DR Congo) through Uganda, arrived in Nairobi on October 3. He later died, marking the first recorded Ebola death in Kenya during the current outbreak.
Although both patients reportedly passed through Entebbe International Airport on the same day, investigators have not confirmed whether they met, used the same facilities or had any other form of contact.
“One of the issues we are currently investigating has been some sort of interaction between the two cases at the airport,” Mankoula told journalists on Thursday.
Authorities are also exploring whether the infections could have originated from a common source rather than resulting from direct contact between the patients.
Dr Patrick Otim, a WHO emergency response official, said investigators had not yet determined where the Nigerian woman contracted the virus.
“The source of exposure is still not known. The travel history of the patient is still being pieced together,” he said.
Otim explained that establishing a complete account of the woman’s movements had been challenging because investigators had limited opportunities to interview her while she remained in hospital.
Genomic Testing and Contact Tracing Underway
The Nigeria Centre for Disease Control and Prevention (NCDC) is conducting genomic sequencing to help determine whether the infection is genetically related to other identified cases.
Dr Pavel Ursu, the WHO representative in Nigeria, said investigators were prioritising efforts to establish the patient’s complete travel and exposure history.
“The investigation is reconstructing the full travel and exposure history. Genomic sequencing is given a high priority,” Ursu said.
Ugandan health officials had earlier indicated that the woman travelled to eastern DR Congo for business, the area where the current Ebola outbreak began.
However, the WHO, Africa CDC and Nigeria’s health ministry said they had not received verified information confirming that she visited the country.
Uganda has maintained that it has no confirmed active Ebola cases, adding that the woman’s passage through its territory does not, on its own, establish where she contracted the virus.
Meanwhile, Nigeria has identified additional individuals who may have been exposed to the infected woman, beyond the 44 contacts initially reported.
According to Mankoula, many of the identified contacts are healthcare workers at facilities where the woman received treatment, alongside a smaller number of family members.
He said Nigerian authorities were working to identify individuals considered to be at high risk and place them under quarantine, but declined to provide an updated figure before the government formally released further details.
Kenya Reports Progress in Containing Outbreak
In Kenya, the first group of individuals quarantined following possible exposure to Ebola is expected to begin returning home on Sunday after completing the 21-day monitoring period without developing symptoms.
Kenya’s Director-General of Health, Dr Patrick Amoth, said all nine confirmed infections were linked to the initial patient, with no evidence of wider community transmission.
“We are not out of the woods,” Amoth warned, urging the public to remain alert while avoiding unnecessary panic.
He added that the remaining eight patients were still receiving treatment in isolation and were responding well.
The developments have renewed concerns about the cross-border movement of infected individuals, particularly between DR Congo and neighbouring Uganda, where thousands of people cross daily for business, employment and family visits.
Dr Otim warned that the extensive and porous border between the two countries presents significant challenges for disease surveillance, as some travellers use unofficial crossing points that are difficult to monitor.
WHO Regional Director for Africa, Dr Mohamed Janabi, called for stronger regional vigilance, urging governments to intensify surveillance, investigate suspected infections and protect frontline healthcare workers.
What You Need to Know About Ebola
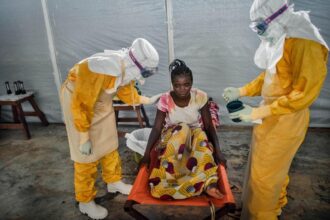
Ebola is a severe viral disease transmitted through direct contact with the blood or other bodily fluids of an infected person, as well as contaminated objects. Unlike influenza, it does not spread through the air under ordinary circumstances.
Symptoms may include fever, extreme weakness, vomiting and diarrhoea, and the disease can be fatal. Infected individuals are generally not considered contagious before symptoms develop.
Health authorities emphasise that rapid contact tracing, the prompt isolation of suspected cases and timely medical care remain essential to limiting transmission and preventing further spread.
Investigations into the possible connection between the Nigerian and Kenyan cases are continuing, with authorities awaiting further epidemiological and genomic evidence to establish whether the infections are linked.